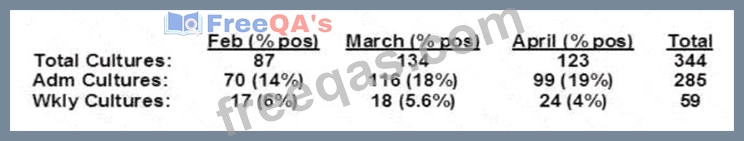
A facility performs active surveillance cultures for methicillin-resistant Staphylococcus aureus (MRSA) on all patients upon admission and weekly. Twenty-two of the patients with positive cultures for MRSA were transferred from outlying facilities. The following MRSA data for a 3-month period are shown. Review of the data reveals which of the following is increasing?
Correct Answer: B
The table separates admission cultures from weekly cultures, which is a common surveillance approach to distinguish imported MRSA burden (present on admission) from healthcare acquisition (newly detected later). The admission culture percent positive rises over the three months: 14% (Feb) # 18% (Mar) # 19% (Apr). That pattern indicates an increasing admission prevalence (option B). NHSN MDRO surveillance methods describe admission prevalence as a proxy measure using admission-related data to quantify organisms present at the time of entry into a location/facility. By contrast, weekly culture positivity-often used as a proxy for on-unit acquisition/transmission when admission screening is in place-decreases: 6% # 5.6% # 4%, so option A is not increasing. The dataset also does not provide information about MRSA infections versus colonization (so C cannot be concluded), nor does it provide a denominator for "compliance" (e.g., expected admissions/weekly screens completed), so D cannot be determined. This interpretation aligns with standard infection prevention use of MRSA surveillance data to track prevalence (burden) versus incidence/acquisition.
Question 7
A patient with suspected active tuberculosis is being transferred from a mental health facility to a medical center by emergency medical services. Which of the following should an infection preventionist recommend to the emergency medical technician (EMT)?
Correct Answer: C
Active tuberculosis (TB) is an airborne disease transmitted through the inhalation of droplet nuclei containing Mycobacterium tuberculosis. Effective infection control measures are critical during patient transport to protect healthcare workers, such as emergency medical technicians (EMTs), and to prevent community spread. The Certification Board of Infection Control and Epidemiology (CBIC) emphasizes the use of appropriate personal protective equipment (PPE) and source control as key strategies in the "Prevention and Control of Infectious Diseases" domain, aligning with guidelines from the Centers for Disease Control and Prevention (CDC). For a patient with suspected active TB, the primary goal is to contain the infectious particles at the source (the patient) while ensuring the EMT is protected from inhalation exposure. Option C, placing an N95 respirator on the patient and a surgical mask on the EMT, is the most appropriate recommendation. The N95 respirator on the patient serves as source control by filtering the exhaled air, reducing the dispersion of infectious droplets. However, fitting an N95 respirator on the patient may be challenging, especially in an emergency setting or if the patient is uncooperative, so a surgical mask is often used as an alternative source control measure. For the EMT, a surgical mask provides a basic barrier but does not offer the same level of respiratory protection as an N95 respirator. The CDC recommends that healthcare workers, including EMTs, use an N95 respirator (or higher-level respiratory protection) when in close contact with a patient with suspected or confirmed active TB, unless an airborne infection isolation room is available, which is not feasible during transport. Option A is incorrect because placing a surgical mask on both the patient and the EMT does not provide adequate respiratory protection for the EMT. Surgical masks are not designed to filter small airborne particles like those containing TB bacilli and do not meet the N95 standard required for airborne precautions. Option B is impractical and unnecessary, as placing an N95 respirator on both the patient and the EMT is overly restrictive and logistically challenging, especially for the patient during transport. Option D reverses the PPE roles, placing the surgical mask on the patient (insufficient for source control) and the N95 respirator on the EMT (appropriate for protection but misaligned with the need to control the patient's exhalation). The CBIC and CDC guidelines prioritize source control on the patient and respiratory protection for the healthcare worker, making Option C the best fit. This recommendation is consistent with the CBIC's emphasis on implementing transmission-based precautions (CDC, 2005, Guideline for Preventing the Transmission of Mycobacterium tuberculosis in Healthcare Settings) and the use of PPE tailored to the mode of transmission, as outlined in the CBIC Practice Analysis (2022). References: CBIC Practice Analysis, 2022. CDC Guideline for Preventing the Transmission of Mycobacterium tuberculosis in Healthcare Settings, 2005.
Question 8
The Sterile Processing Deportment alerts an infection preventionist that a load of surgical Instruments sterilized with high temperature steam:moist heat needs to be recalled. Which of the following Is the MOST likely reason for the recall?
Correct Answer: B
The most likely reason for the recall of a steam-sterilized load is the failure of the biological indicator (BI), specifically Geobacillus stearothermophilus, which is used to monitor high-temperature steam (moist heat) sterilization processes. This organism is the biological indicator of choice because it has high resistance to moist heat and thus serves as a reliable marker for sterilization efficacy. The APIC Text and AAMI ST79 guidelines confirm that Geobacillus stearothermophilus is used for steam sterilization and that a failed BI indicates a failure in the sterilization process, which requires immediate action, including recalling all items sterilized since the last negative BI and reprocessing them. This is a crucial aspect of ensuring patient safety and preventing the use of potentially non-sterile surgical instruments. According to the APIC Text: "BIs are the only process indicators that directly monitor the lethality of a given sterilization process. [...] Geobacillus stearothermophilus spores are used to monitor steam sterilization..." The CIC Study Guide (6th ed.) also specifies that: "Evidence of sterilization failures (e.g., positive biological indicators) is the most common reason for a recall." Additionally, it is noted: "With steam sterilization, the instrument load does not need to be recalled for a single positive biological indicator test, with the exception of implantable objects." However, multiple positive BIs or BI failure confirmation does require a recall. The incorrect options explained: A). Bacillus subtilis - This is not used in steam sterilization but rather in dry heat or EO processes. C). Placement of the biological indicator on the bottom shelf over the drain - While incorrect placement can lead to test failure, the recall is prompted by BI failure, not just placement. D). Incorrect placement of instruments - This can cause sterilization failure but is not the direct trigger for a recall unless it leads to a failed BI. References: CIC Study Guide, 6th Edition, Chapter 10 - Cleaning, Sterilization, Disinfection, Asepsis, Pages 211, 236 APIC Text, 4th Edition, Chapter 106 - Sterile Processing ANSI/AAMI ST79:2017, cited throughout APIC Text and APIC 4 for sterilization monitoring protocols.
Question 9
An outbreak of carbapenem-resistant Klebsiella pneumoniae is linked to duodenoscopes. What is the infection preventionist's PRIORITY intervention?
Correct Answer: B
* The CDC and FDA have identified duodenoscopes as high-risk devices due to inadequate reprocessing, leading to MDRO transmission. * The first priority is enhancing reprocessing protocols and ensuring strict compliance with manufacturer instructions. CBIC Infection Control References: * APIC Text, "Endoscope Reprocessing and Infection Risk," Chapter 10.
Question 10
Given the formula for calculating incidence rates, the Y represents which of the following?
Correct Answer: C
Incidence rate is a fundamental epidemiological measure used to quantify the frequency of new cases of a disease within a specified population over a defined time period. The Certification Board of Infection Control and Epidemiology (CBIC) supports the use of such metrics in the "Surveillance and Epidemiologic Investigation" domain, aligning with the Centers for Disease Control and Prevention (CDC) "Principles of Epidemiology in Public Health Practice" (3rd Edition, 2012). The formula provided, XY×K=Rate\frac{X} {Y} \times K = RateYX×K=Rate, represents the standard incidence rate calculation, where KKK is a constant (e.g., 1,000 or 100,000) to express the rate perunit population, and the question asks what YYY represents among the given options. In the incidence rate formula, XXX typically represents the number of new cases (or events) of the disease occurring during a specific period, and YYY represents the population at risk during that same period. The ratio XY\frac{X}{Y}YX yields the rate per unit of population, which is then multiplied by KKK to standardize the rate (e.g., cases per 1,000 persons). The CDC defines the denominator (YYY) as the population at risk, which includes individuals susceptible to the disease over the observation period. Option B ("Number of infected patients") might suggest XXX if it specified new cases, but as the denominator YYY, it is incorrect because incidence focuses on new cases relative to the at-risk population, not the total number of infected individuals (which could include prevalent cases). Option C ("Population at risk") correctly aligns with YYY, representing the base population over which the rate is calculated. Option A, "Population served," is a broader term that might include the total population under care (e.g., in a healthcare facility), but it is not specific to those at risk for new infections, making it less precise. Option D, "Number of events," could align with XXX (new cases or events), but as the denominator YYY, it does not fit the formula's structure. The CBIC Practice Analysis (2022) and CDC guidelines reinforce that the denominator in incidence rates is the population at risk, ensuring accurate measurement of new disease occurrence. References: CBIC Practice Analysis, 2022. CDC Principles of Epidemiology in Public Health Practice, 3rd Edition, 2012.